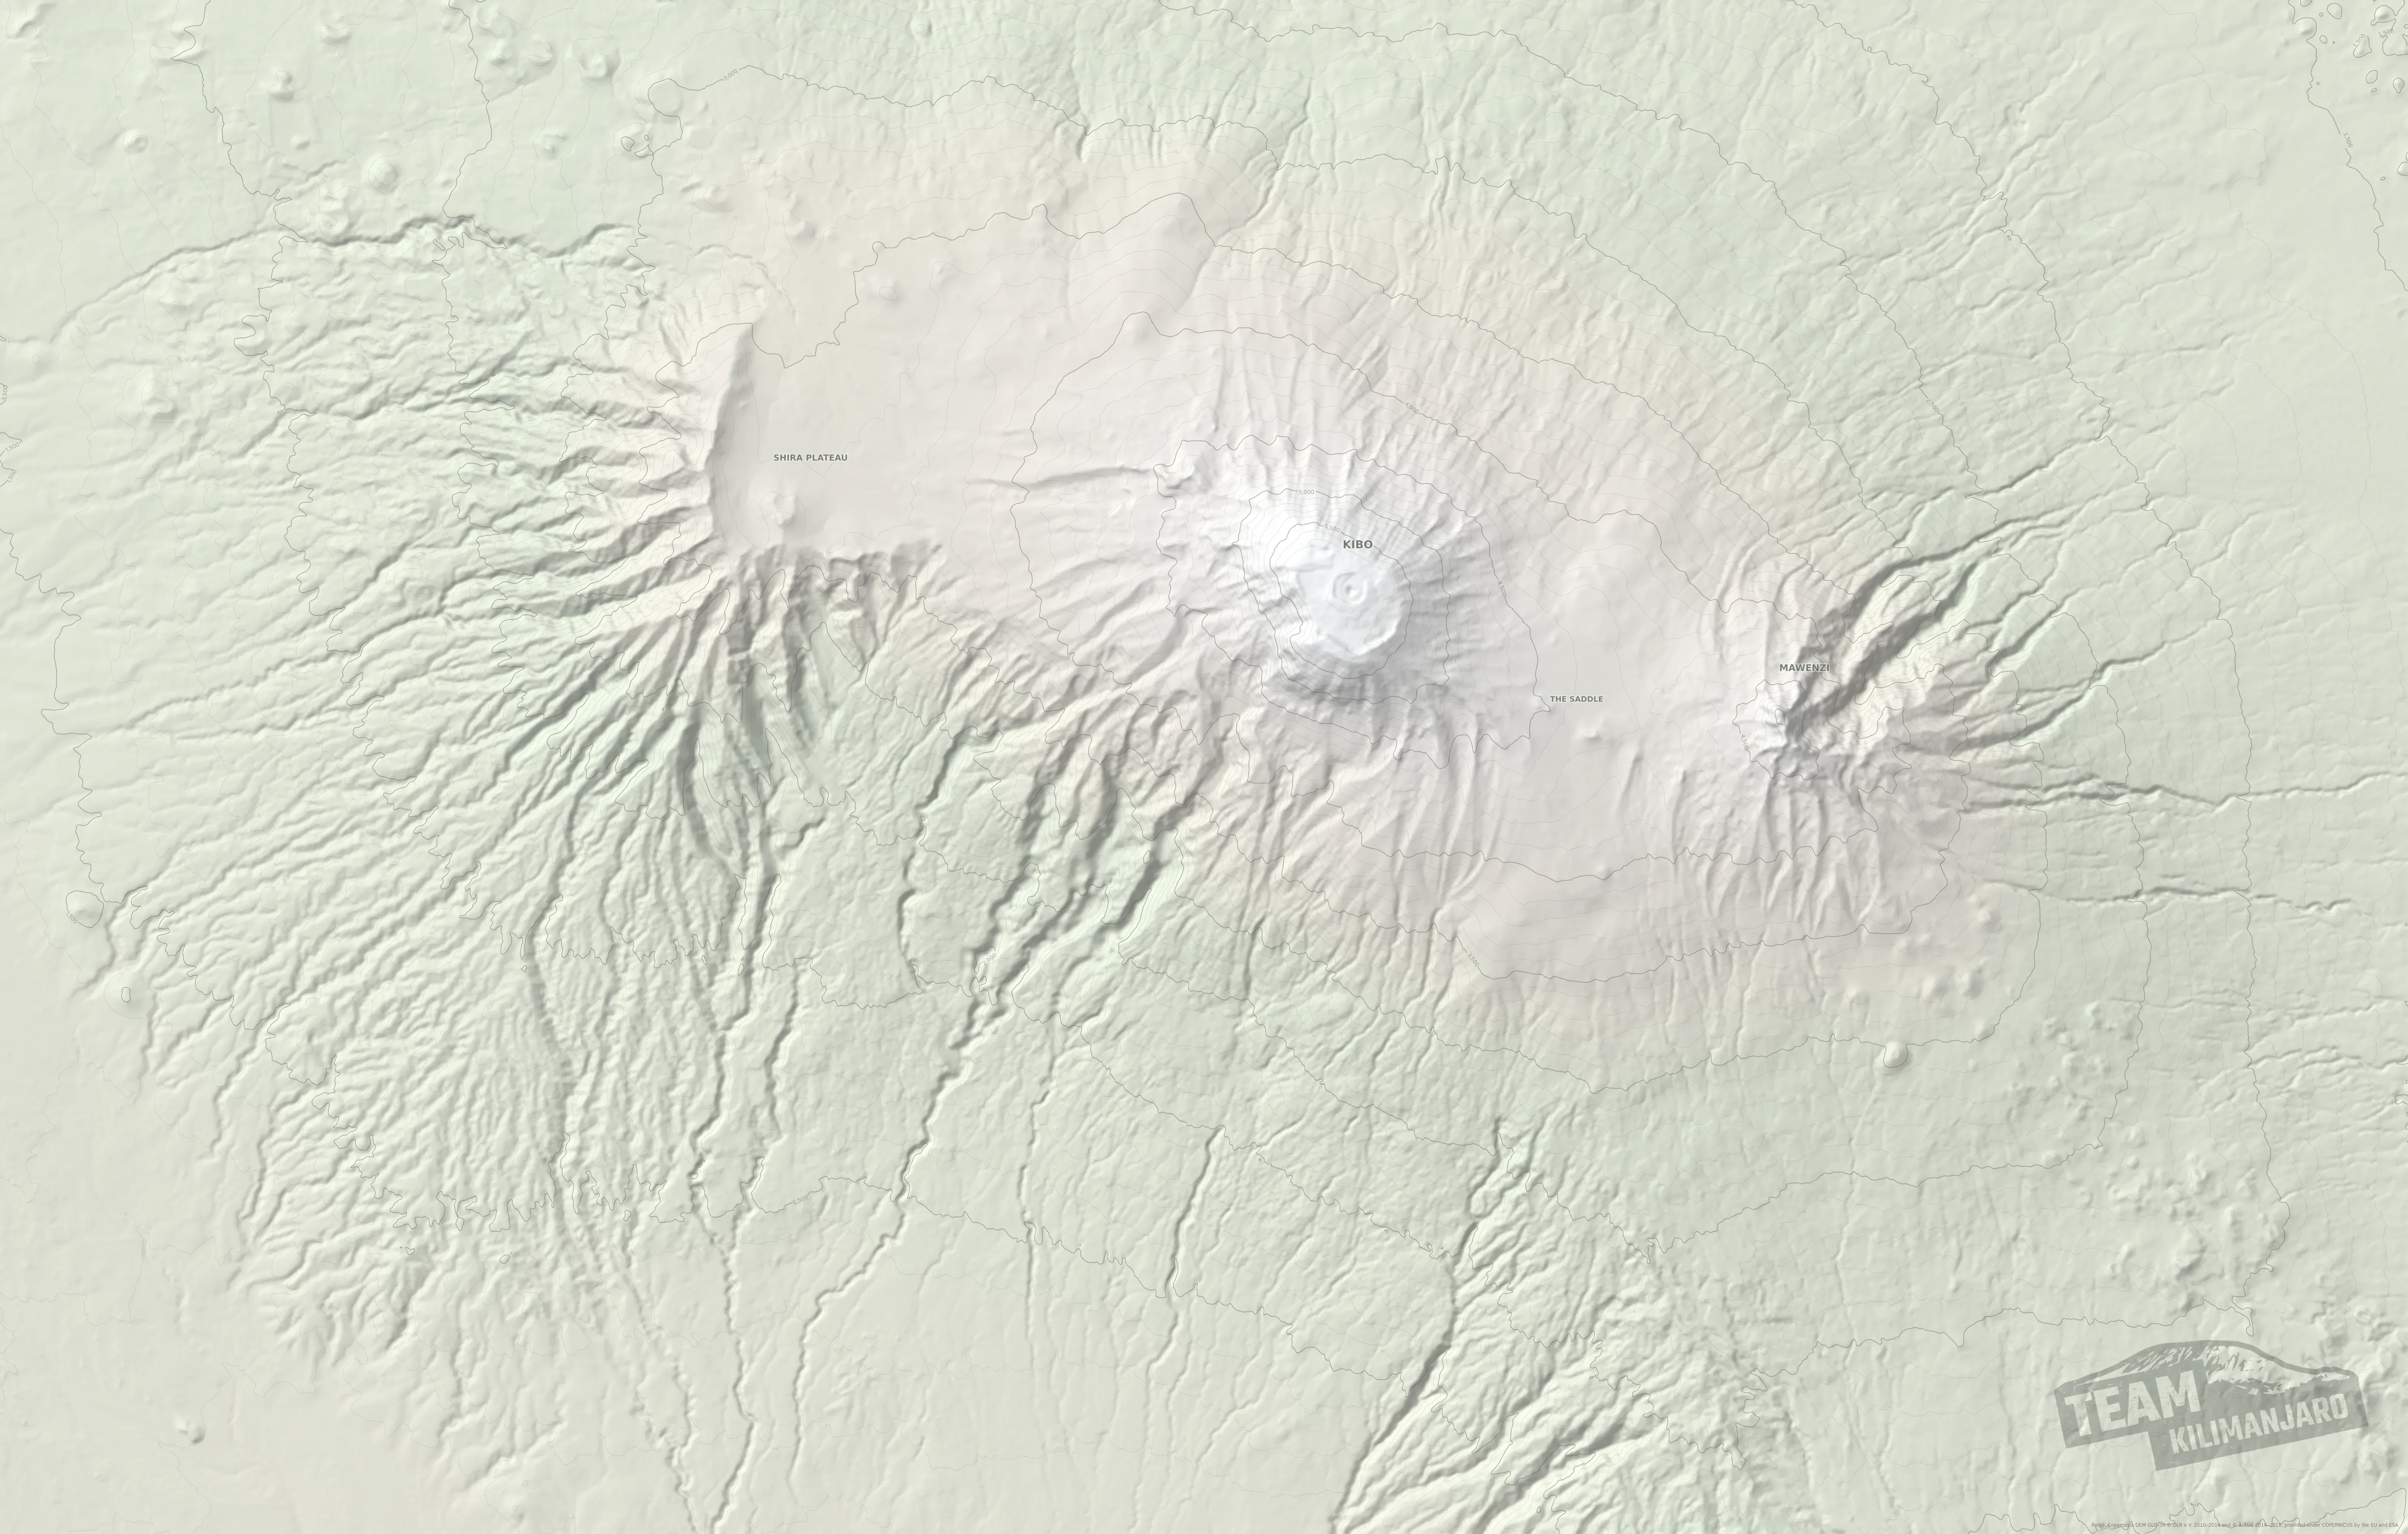
The busiest camping route, climbing from the southern rainforest onto the Shira Plateau before traversing beneath the Southern Icefields. 56.7 km round trip.
The quietest start, from the western forest onto the Shira Plateau. The standard route joins Machame beyond Shira 2; TK Lemosho, our own variation, takes the quiet northern circuit and summits from School Hut. 64.7 or 66.4 km round trip.
Starts high on the Shira Plateau, reached by vehicle: only for climbers already acclimatised, for example after Mount Meru. Seven or eight days, or joined to TK Lemosho.
From the north, near the Kenyan border. The Rongai most companies run crosses the Saddle to Kibo Hut; TK Rongai, our own, climbs over the Mawenzi ridge and summits from School Hut. 68.0 or 72.2 km round trip.
It can be. By our estimate around thirty people die on Kilimanjaro in a typical year, a death rate of roughly one for every thousand who attempt the summit. Most of those deaths are recorded as altitude sickness, but in our experience the records hide a second killer: heart failure.
With an attentive guide, a route designed for acclimatisation and the decision to descend made early, the risk is very low. This page explains what the real dangers are, what actually keeps you safe, and what does not.
About 30Deaths a year, our estimate
1 in 1,000Of those attempting the summit
300 mOf descent usually relieves oedema
2006We led the Western Breach investigation
By John Rees-Evans, founder of Team Kilimanjaro, who led the park authority’s investigation into the 2006 Western Breach rockfall.
DescendIt is not equipment that saves lives on Kilimanjaro, but guides who act early
The risks, in proportion
I was at a drop zone with friends when one of them read out a message: a friend of his, a young father who had parachuted for years, had been killed that day. Having just jumped myself, I assumed a parachuting accident. It was a road accident, on his way home from a distant work assignment.
We take driving for granted because we have done it since childhood, yet steering a tonne of metal within inches of another coming the other way, with a phone ringing or children arguing, is genuinely dangerous. Somehow it rarely crosses our minds.
So, while climbing Kilimanjaro certainly has its dangers, they are best seen in context. A few companies exaggerate them to frighten climbers towards themselves. I would rather tell you plainly where the real risks lie.
Swipe sideways to see every column. Tap i for more detail.
Kilimanjaro’s death rate, and what the records hide
Nobody publishes an official death toll for Kilimanjaro, and the figures you will read elsewhere vary widely. These are ours, from our seasons on the mountain since 2004.
About 30Deaths on Kilimanjaro in a typical year, by our estimate
1 in 1,000Of those who attempt the summit: a death rate of roughly 0.1%
Often wrongThe cause of death on the certificate, in our experience
What the death certificates say
When someone dies on Kilimanjaro, they are taken to KCMC hospital in Moshi. In our experience, once the hospital is told that the death happened on the mountain, it records the cause as acute mountain sickness, without investigating further. We have tried to persuade the hospital to look more carefully, without success. Two of our own cases show what this hides.
One of our clients
A heart rate that slowed as he climbed
When one of our clients died on the mountain, we knew what the certificate would say, and how it would distress his family to read that his death had been easily avoidable. So we flew a colleague out from the UK to retrieve his heart-rate watch and read its data.
As he climbed higher, his heart rate had slowed steadily: the opposite of what we normally see at altitude, where it rises. It was heart failure. His family arranged their own post-mortem when he was brought home, and it confirmed heart failure.
A climber died of heart failure after being evacuated from just 3,100 m, a height at which fatal altitude illness is very rare. His brother had died of heart failure when quite young.
A family history like that is exactly the warning a correct cause of death would give the relatives who are still living.
A death from heart failure often reveals a hidden condition, sometimes an inherited one. Record it as altitude sickness and the relatives never learn that they too should have their hearts checked, when that knowledge could save their lives.
For future climbers
If every death is put down to altitude, deaths look unavoidable, and climbers see no reason to test their hearts before they come. Many of these deaths could be prevented by a proper check at home.
For the picture of guiding
A death from altitude sickness suggests a guide who missed the signs. Misrecorded causes make guiding look far more dangerous than it is, and some operators use that impression to frighten climbers away from local companies.
Have your heart checked before you climb. If you are over 50, or anyone in your family has had heart trouble or died suddenly when young, ask your doctor for a thorough cardiac assessment before you book flights, and tell them you will be climbing to 5,895 m. Ask whether a resting ECG is enough, or whether an exercise test or a heart scan would be wiser. On the mountain, tell your guide at once if your heart rate seems unusually slow.
The dangers of climbing Kilimanjaro
Mountaineering is inherently dangerous. These are the dangers that matter on Kilimanjaro, in the order I worry about them.
The main risk
Acute mountain sickness
Probably three in every four trekkers feel some degree of acute mountain sickness (AMS): it is very rare not to have at least a mild headache or a touch of nausea, the earliest symptoms. A well-designed route, an attentive guide, and good food, fluids and rest make sure that for the great majority it stays mild, if it appears at all.
If AMS is hidden from the guide and the climber keeps going up, it can develop into pulmonary oedema (HAPE) or cerebral oedema (HACE): fluid in the lungs or brain, the body’s response to a critically low oxygen supply. Left untreated, either can kill.
Yet for a well-trained team, Kilimanjaro is probably one of the safest mountains over 5,000 m on which to meet this threat, because from almost anywhere on every permitted route you can descend quickly. Caught early, a descent of just 300 m usually lets the climber walk on unaided, though we keep assisting for at least a further 1,000 vertical metres.
Mainly one route
Rockfall
On the summit paths above Barafu and Kibo Hut, heavy traffic on loose scree means some rockfall on every standard route, but it rarely bounces higher than thigh height. The Western Breach is different: there, rock can bounce well above head height, and it is lethal.
Often hidden, often misrecorded
Heart failure
My greatest concern at altitude is the climber with an undiagnosed heart condition. You may not know you have one until your first time at altitude, which is not the place to find out. If you are over 50, ask your doctor to test your heart thoroughly, and think about any condition you may have inherited. On the mountain, be suspicious of a heart rate that becomes unusually slow.
In my experience it is extremely unlikely that a client will die of cold or exhaustion. Even the least capable guide who has managed to qualify for a licence is unlikely to push a client to collapse, or to miss that someone is so cold they are losing consciousness.
What I learned on the Western Breach
In January 2006, rockfall killed three climbers on the Western Breach. The park authority asked me to lead their officials into the hazard zone, find the cause and recommend what to change. I found one of the climbers’ bandanas, and it was clear the falling rock had bounced to head height.
The route had been laid out on a mistaken belief, shared by everyone, about where the rockfall on that face came from. To see for myself, I spent a cold night at 5,300 m without a tent, halfway up the Breach, so that I could watch the path the rocks took without first having to climb out of a tent. Fragments the size of medicine balls bounced continuously three to five metres high, falling at around 60 to 80 miles an hour.
The route was reconfigured on my recommendations. Even so, it is far from guaranteed safe: a guide must cross its gullies quickly, at right angles and in the correct way, and even then a rock can come down in those few seconds. Anyone climbing it should be very cautious. The Western Breach in detail 👉
What actually keeps you safe
You are only as safe as your guide’s ability to spot the early signs that you are heading for serious altitude illness, and his decisiveness in getting you down, with an assistant guide if the rest of the group carries on. Our guides are very attentive, and they are in contact with our office every day they are on the mountain, unless the weather is unusually bad.
Our own routes, TK Lemosho and TK Rongai, are built for acclimatisation, with climb-high, sleep-low days that the standard routes lack. Fewer climbers become seriously ill in the first place.
It is not hardware that saves lives on Kilimanjaro, but guides who carry out practised procedures without hesitating.
An evacuation, 16 October 2007
At 5,200 m, our guide Deodatus Na’alli judged that a climber with a lifelong disability, on what became a world-record ascent, needed to descend immediately.
05:45Descent begins from close to the summit, while our office alerts the park warden
11:50The climber is in an ambulance we asked to drive up to 2,300 m
12:30Receiving care at KCMC hospital in Moshi: 6 hours 45 minutes in all
He recovered fully, and has since encouraged many others to take on the climb.
Safety equipment: what helps and what does not
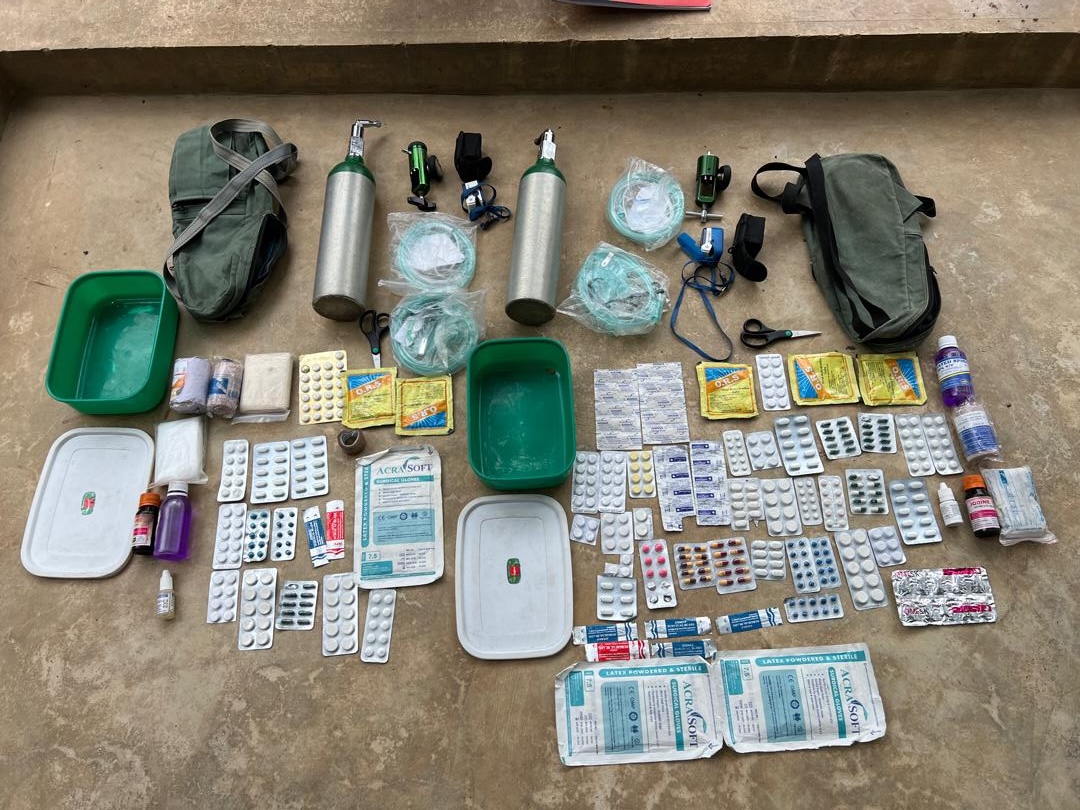
Some operators advertise kit as if it were insurance against death. It is not, and relying on it can make guides slower to do the one thing that works: descend. We carry what is useful and say plainly what is not.
Oxygen
Carried on every climb, for emergencies only
Given with rapid descent, never to help a climber to the summit: breathing it on the way up switches off the body’s adaptation, and leaves you exposed if it runs out.
Gamow bags
Available, USD 30 a day
Excellent on Everest, where descent can take days. On Kilimanjaro, setting one up wastes time better spent descending: from Stella Point two crew can take a climber down 300 to 450 m in thirty minutes.
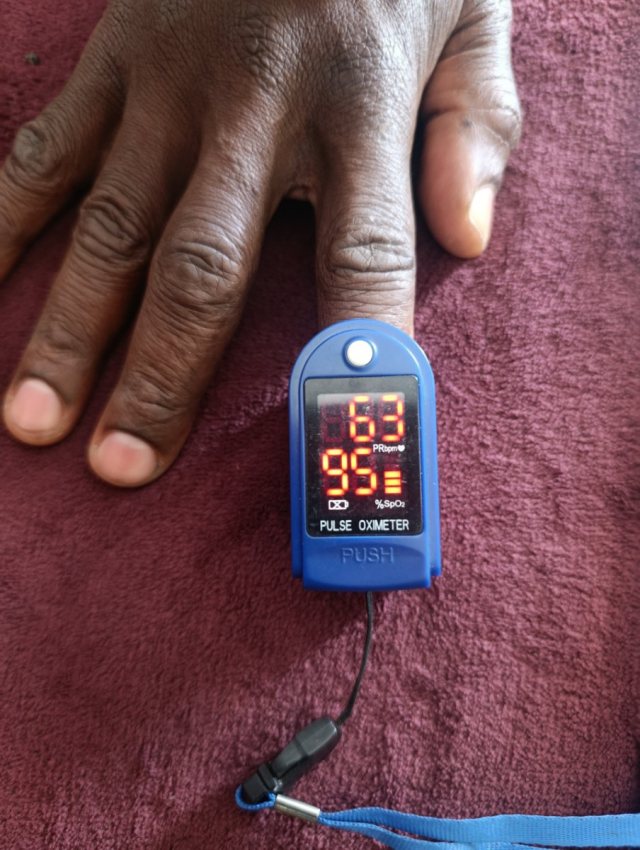
Pulse oximeters
Carried on every climb, daily use discouraged
Readings mislead: a fit, well-acclimatised athlete can read 70% at Barafu while an unfit climber reads 80%, and cerebral oedema can develop at 80%. An experienced guide’s eye is the better tool.
Defibrillators
Available, USD 30 a day
Life-saving at sea level, but we have yet to hear of one saving a life on a high expedition, and resuscitation in the crater’s thin air risks lasting brain damage. Groups who want one must agree to indemnify our staff.
You may have read the Royal Geographical Society’s rule of no more than 300 m a day, with two nights at the same height every third day, which would mean ten days on Kilimanjaro. As you may know, the same society once refused to believe there could be snow on Kilimanjaro, because the missionaries who reported it were not scientists.
Thousands of climbers reach the summit safely every year without following that rule. The days matter less than how they are used: a route that climbs high and sleeps low, at a pace your guide adjusts to you. We recommend seven or eight days for most climbers.
Our Excel series adds a night camped in the crater at 5,725 m. There is a small but real risk of severe AMS, HAPE or HACE when sleeping that high, so we always reach the summit first and then come down to sleep in the crater, keeping to the rule of climbing high and sleeping low.
Around one in five of those who ask for the crater night change their minds on the mountain, after agreeing with their guide that they are not well enough acclimatised for it. Please weigh that before you choose it.
Your part in staying safe
Check your heart
Over 50, or anyone in your family with heart trouble or a sudden early death? Ask your doctor for a thorough cardiac check before you book flights.
Tell your guide everything
Headache, nausea, breathlessness at rest, unusual tiredness. Hiding symptoms is how mild AMS becomes dangerous.
Take your time
Choose enough days, walk slowly, drink well and eat even when you don’t feel like it.
Choose your route
Avoid rockfall zones unless you understand the risk, and prefer a route that climbs high and sleeps low.
Insure properly
Make sure your travel insurance covers trekking to 6,000 m and helicopter evacuation.
Train
A fitter climber has more in reserve and notices more. Our training plan
Questions about safety on Kilimanjaro
How many people die on Kilimanjaro each year?
By our estimate, around thirty: roughly one for every thousand people who attempt the summit.
No official figure is published, and the estimates you will read elsewhere vary widely. Ours, from our seasons on the mountain since 2004, is around thirty deaths a year, or about one for every thousand climbers attempting the summit. Most are recorded as altitude illness, but in our experience the recorded cause is not reliable: we have seen heart failure recorded as altitude sickness without any investigation. What the death certificates don’t tell you 👉
What is the death rate on Kilimanjaro?
About one in every thousand climbers who attempt the summit, by our estimate.
That is a death rate of roughly 0.1%. No official figure is published, so treat any precise number you read, including ours, as an estimate. What matters more is that many of these deaths are avoidable: by recognising altitude illness early and descending at once, and by climbers having their hearts properly checked before they come.
What do people die of on Kilimanjaro?
Altitude illness and heart failure, though the records blur the two.
Altitude illness that is hidden or ignored can turn into fluid on the lungs or brain (HAPE or HACE), and that kills. But when anyone dies on the mountain, the cause is usually recorded as acute mountain sickness, whatever actually happened, so heart failure is under-counted. If you have any doubt about your heart, have it checked before you climb.
Are there dead bodies on Kilimanjaro?
No. Anyone who dies is brought down.
Unlike the highest Himalayan peaks, every part of Kilimanjaro’s trekking routes can be reached by rescue teams, so anyone who dies on the mountain is carried down, usually to KCMC hospital in Moshi.
Which is the most dangerous route?
The Western Breach, because of rockfall.
On the Western Breach, falling rock can bounce above head height, and three climbers were killed there in January 2006. The route was reconfigured after the investigation I led, but it still demands caution and a guide trained to cross the gullies quickly and correctly. The Western Breach in detail 👉
Is Kilimanjaro safe for beginners?
Yes, with a good team and enough days. You need no climbing experience.
Kilimanjaro is a trek, not a technical climb, and most of our climbers have never been to altitude before. What matters is a route with enough days to acclimatise, a guide who watches you closely, and your own honesty about how you feel. We recommend seven or eight days for a first climb.
Do I need oxygen to climb Kilimanjaro?
No. We carry it for emergencies only, together with descent.
Breathing bottled oxygen on the way up switches off the body’s own adaptation to altitude, and leaves you dangerously exposed if the supply runs out. We carry oxygen on every climb, the same canisters and regulators supplied to the US State Department, but we use it only in an emergency, alongside rapid descent.
Is there helicopter rescue on Kilimanjaro?
Sometimes, but it cannot be relied on.
Only one helicopter operator is currently licensed for evacuations from Kilimanjaro, and it can fly only in clear weather. When cloud or wind rule out a flight, a casualty is carried down by stretcher, typically at around 500 vertical metres an hour. Check that your travel insurance covers helicopter evacuation before you fly.
What happens if I get altitude sickness on one of your climbs?
Mild symptoms are common and watched closely; serious ones mean immediate descent.
Most climbers feel a mild headache or a little nausea at some point, and your guide will watch these closely, adjusting your pace, rest and fluids. If the signs point to something more serious, the response is immediate descent with an assistant guide, while our office arranges any onward evacuation. Acute mountain sickness explained 👉
In short: climb with a competent team, avoid rockfall zones, choose a route designed to acclimatise you, drink plenty, and don’t rush. Do that, and the risks of climbing Kilimanjaro are really very low. John Rees-Evans
Questions about your own safety?
Tell us about your health, fitness and experience, and we will recommend the route and length that suit you, and answer anything that worries you.